
 Tetracycline in Acne Treatment: Benefits and Limitations
How Tetracycline Fights Acne: Mechanisms Explained
Listening to patients, clinicians explain that tetracycline attacks acne on two fronts: antimicrobial action against Cutibacterium acnes by blocking the bacterial 30S ribosomal subunit and reducing protein synthesis, and anti-inflammatory effects that blunt neutrophil chemotaxis and cytokine release. This duality often feels reassuring to people who receive an Rx, because bacterial load and inflammation shrink together, and lesions flatten.
Tetracyclines also modulate matrix metalloproteinases and inhibit biofilm formation, improving healing. Side benefits include reduced sebum-related irritation and fewer cystic flares. Patients should ask pharmacists or a Pharm Tech about generics, interactions, and photosensitivity precautions; clinicians weigh anti-infective potency against resistance risks when choosing long courses. They monitor response and stop therapy once inflammation clearly subsides.
| Mechanism | Effect |
|---|---|
| 30S ribosome binding | Reduces C. acnes growth |
| Anti-inflammatory action | Decreases lesion redness and swelling |
Proven Clinical Benefits and Effectiveness in Studies
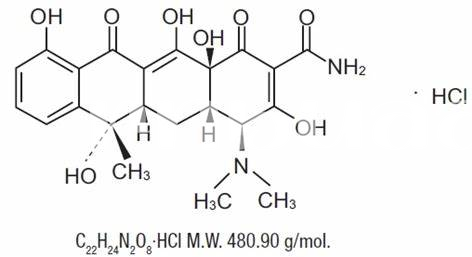
Large trials demonstrate that tetracycline and related agents lower inflammatory acne lesions and improve patient reported outcomes within weeks and scarring progression risk.
Meta analyses confirm moderate to large effect sizes versus placebo for inflammatory acne; benefits extend when combined with topical retinoids.
Typical studies used oral doxycycline or minocycline, with measurable decreases in lesion counts and sebum associated markers; adherence and proper Rx selection influenced results.
Longer trials emphasize relapse risk after stopping, supporting combined maintenance with topical therapies and use of Generics to reduce cost and improve access.
Typical Dosing, Duration, and Practical Treatment Tips
Starting tetracycline can feel like a rebellion: steady pills, visible change. Clinically it targets bacteria and inflammation, so early weeks often bring modest improvement while skin calms.
Typical approaches balance effective dose and safety; many clinicians aim for several weeks to months, then reassess. Short courses limit resistance, while extended therapy requires clear goals and monitoring.
Practical tips help: take tetracycline away from dairy, calcium, iron and antacids to preserve absorption, and avoid tanning beds because of photosensitivity. Keep consistent timing, and report severe stomach upset or rash.
Discuss cost and formulation — generics lower cost — and request an Rx with clear sig and follow-up plan. Adherence, check-ins, and early switching if no benefit optimize outcomes.
Common Side Effects and Long-term Safety Considerations
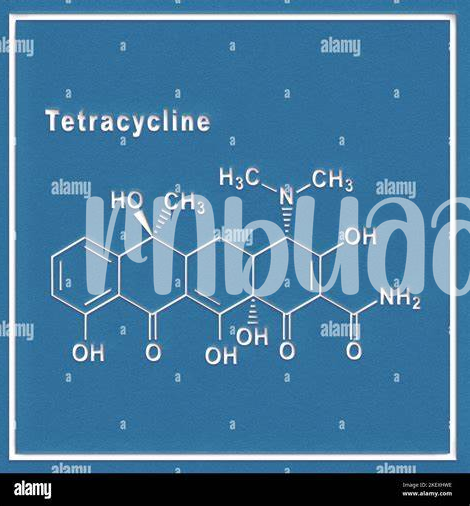
Patients often find tetracycline quickly reduces inflammatory acne, but common complaints include gastrointestinal upset, photosensitivity and candidal overgrowth; mild nausea or diarrhea may prompt dose timing adjustments.
Less frequent but important toxicities include hepatotoxicity, intracranial hypertension and vestibular symptoms; clinicians usually recommend baseline liver tests and counsel about sun protection, pregnancy avoidance and dental staining risk in children. Ask your provider for an Rx - Prescription that includes clear Sig - Directions on a prescription to improve adherence.
Long-term use alters flora and raises resistance concerns, so limit duration, pair with topical agents or isotretinoin when indicated, and favor periodic medication review to reassess need; choose Generics - Non-brand medications when cost matters and monitor for persistent side effects. Document allergies, avoid co-prescribing with oral retinoids without specialist input, and schedule regular follow-up visits to track response and adverse events.
Antibiotic Resistance Risks and Responsible Prescribing Practices
Resistance isn’t an abstract threat; stories from clinics show formerly reliable tetracycline courses failing as bacterial populations adapt. Patients expecting quick clears can unintentionally fuel resistance by stopping therapy early or requesting redundant long courses, while casual sharing or Pharm Party behavior spreads leftover meds. Clinicians must narrate risks clearly so choices align with public health.
Stewardship means targeted Rx - Prescription, short effective durations, culture-guided switches, and prioritizing Generics - Non-brand medications when appropriate to limit selection pressure. Shared decision-making, documentation, and surveillance reduce collateral harm; audits and utilization review programs help maintain standards. Education, avoidance of unnecessary long-term monotherapy, and prompt switching to non-antibiotic options when feasible preserve future efficacy in practice.
| Stewardship |
When to Switch Therapies: Alternatives and Combined Strategies
Patients often reach a turning point when antibiotics no longer deliver clear improvement or cause side effects; clinicians weigh acne severity, scarring risk, and patient preference before changing course. Switching may mean stopping systemic tetracycline and moving to hormonal therapy, isotretinoin, or topical retinoids plus benzoyl peroxide — all with informed consent and careful follow-up.
Combination strategies can extend benefit while reducing antibiotic exposure: short oral courses followed by a topical 'cocktail' of retinoid plus benzoyl peroxide, or an Rx for hormonal agents in appropriate patients. Monitor response every 6 to 12 weeks, adjust dosing (titration), and consider derm referral for persistent disease to balance efficacy, safety, and resistance concerns and include periodic lab monitoring.


